Kidney Cancer (Renal Cell Carcinoma): Stages, Diagnosis, Types and Treatment Options
Hi everyone, I’m Dr. Yusuf Saifee, a urologist, uro-oncologist, laparoscopic and robotic surgeon.
Today we are going to talk about kidney cancer, also known as renal cell carcinoma.
The reason I decided to discuss this topic is because I see many patients with kidney tumors. Some patients come with a small kidney mass, while others are diagnosed when the cancer has already reached an advanced stage.
So I thought it would be useful to explain this topic in detail because my goal is to prepare you so that when you see your doctor, you know exactly what’s going on and what questions to ask.
We are going to talk about kidney anatomy, risk factors, staging, the different types of renal cell carcinoma, genetic testing, surgery and other treatment options.
And throughout this discussion, I am also going to tell you some questions that I would ask if I had kidney cancer myself.
These are important questions, and I think every kidney cancer patient should know the answers.
First, Let’s Understand the Anatomy of the Kidney
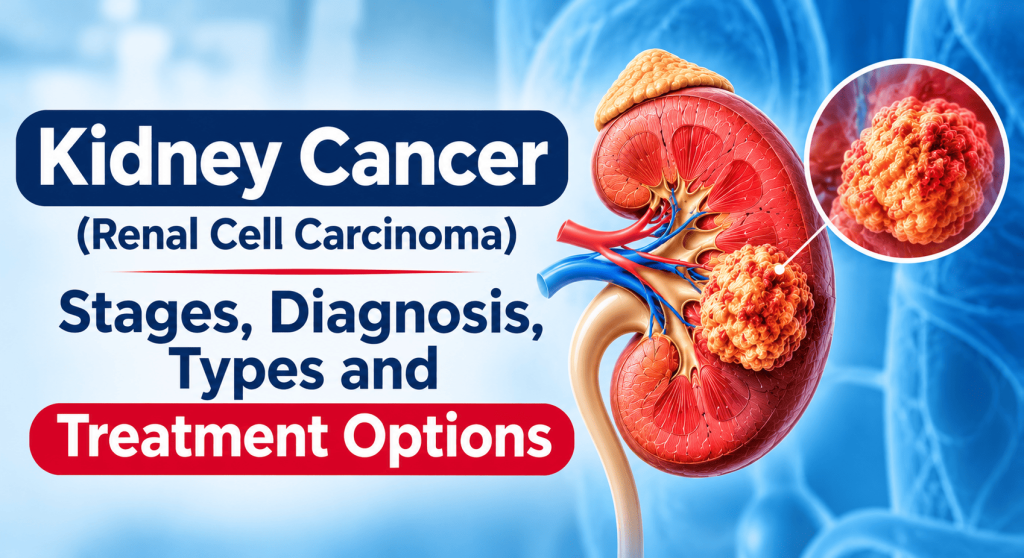
So this is our kidney.
Sitting on top of the kidney, we have our adrenal gland. This is a small triangular-shaped gland that makes hormones.
Now, you know that our kidneys make urine.
We have an artery that brings blood into the kidney. Our kidney filters the blood, makes urine, and then the filtered blood returns to the body through our veins.
The urine that our kidneys make goes into small structures called renal calyces, which eventually drain into the renal pelvis.
From there, urine passes through the ureter, which is a tube that takes urine into the bladder.
Around the kidney, we also have lymphatic vessels and lymph nodes.
Our body is full of lymph nodes, and you need to know this because cancer can spread to these lymph nodes.
That’s the reason I am mentioning them.
Now, the last thing I want you to remember is that our kidneys are surrounded by fat.
That fat protects the kidney.
And around this fatty tissue, we have a membrane called Gerota’s fascia.
This fascia surrounds the kidney and its surrounding fat.
You need to remember this because when we discuss staging, I am going to mention Gerota’s fascia again.
What Are the Risk Factors for Kidney Cancer?
Kidney cancer is more common in older adults, although it can occur at younger ages as well.
The median age at diagnosis is around the mid-60s in many populations.
Now, when we talk about risk factors, we mean things that can increase your chances of developing kidney cancer.
The important ones are smoking, obesity, hypertension and chronic kidney disease.
For example, if you already have certain types of kidney disease, particularly advanced kidney disease, this can also increase your chances of developing kidney cancer.
And the last one would be a strong family history or genetics.
So if somebody in your family has had kidney cancer, particularly at a younger age, that is something you should tell your doctor.
Another important thing I want you to know is that a large proportion of kidney cancers are detected incidentally.
What does incidentally mean?
For example, a patient undergoes sonography or a CT scan for some other reason.
Maybe he has abdominal pain, kidney stones or some other problem.
And during that investigation, the radiologist finds a mass in the kidney.
The patient had no symptoms related to kidney cancer, but the tumor was detected during the scan.
I see this quite often.
So if your kidney tumor was detected accidentally during a scan, you’re certainly not alone.
Where Does Kidney Cancer Usually Spread?
Kidney cancer, like other cancers, can spread to other parts of the body.
This is what we call metastasis.
Now, it’s important to know which organs kidney cancer commonly spreads to.
The common sites are:
- Lungs
- Bones
- Liver
- Brain
- Adrenal glands
- Lymph nodes
There are other sites where kidney cancer can spread, but these are some of the more common ones.
So when we are performing CT scans or MRI scans, these are the areas we may need to evaluate, depending on the patient’s stage and symptoms.
How Do We Find Out the Stage of Kidney Cancer?
This brings us to staging.
Staging basically means the tests we perform to find out how advanced your kidney cancer is.
Is the cancer limited to the kidney?
Has it grown into the surrounding tissues?
Has it entered the blood vessels?
Or has it spread to other organs?
These are the things we want to know.
And for this, imaging tests are very important.
CT Scan and MRI for Kidney Cancer
The most commonly used investigation is a contrast-enhanced CT scan of the abdomen and pelvis, along with imaging of the chest.
Sometimes we use an MRI scan, particularly when we need more information about the kidney mass or the involvement of blood vessels.
Now,
Why is contrast important?
Because kidney tumors often show a characteristic pattern of enhancement after contrast is given.
The radiologist, who is the doctor reading these scans, may tell you that the mass in the kidney is highly suspicious for renal cell carcinoma.
Of course, we also need to consider the patient’s kidney function and whether contrast can be given safely.
Do We Need a Bone Scan?
Sometimes.
Let’s say a patient has persistent bone pain, or the CT scan shows something suspicious in the bone.
In such cases, we may consider additional imaging, including a bone scan or MRI, depending on the situation.
But a bone scan is not routinely required for every kidney cancer patient.
Do We Need an MRI of the Brain?
Again, not for every patient.
But suppose a patient has headaches, blurred vision, seizures or problems with coordination.
These symptoms may make us suspicious that something is happening in the brain.
In that situation, we may advise an MRI of the brain, preferably with contrast when appropriate.
What About PET Scan for Kidney Cancer?
PET scans are commonly used in many types of cancer.
A PET scan uses a radioactive tracer to identify areas of abnormal metabolic activity.
But for renal cell carcinoma, a routine FDG PET scan is not as useful as it is for some other cancers.
So PET scans are not commonly used for initial staging of kidney cancer.
In most patients, CT and MRI remain the main investigations.
What Are the Four Stages of Kidney Cancer?
Kidney cancer is divided into four stages.
Stage 1 is the earliest stage, whereas stage 4 is the most advanced.
And the most important question I want you to ask your doctor is:
“What stage of kidney cancer do I have?”
You need to know whether it is stage 1, 2, 3 or 4 because the treatment will vary depending on the stage.
Stage 1 Kidney Cancer
Stage 1 means that you have a tumor that is 7 cm or less in size and is confined to the kidney.
So, for example, you may have a mass anywhere inside the kidney.
It is not invading surrounding tissues, lymph nodes or distant organs, and its size is 7 cm or less.
That is stage 1.
Stage 2 Kidney Cancer
Stage 2 is similar, except that the tumor is greater than 7 cm.
The tumor is still confined to the kidney.
It has not spread to the surrounding tissues, lymph nodes or other organs.
Stage 3 Kidney Cancer
Stage 3 is a little more advanced.
It can mean that the cancer has involved certain major veins, the tissue around the kidney or nearby lymph nodes.
Remember the fatty tissue around the kidney that I mentioned earlier?
The cancer may extend into that tissue.
But it has not gone beyond Gerota’s fascia.
And there is no distant metastasis.
Stage 4 Kidney Cancer
Stage 4 is the most advanced stage.
It may mean that the cancer has spread to distant organs, such as the lungs, bones, brain or liver.
Or the tumor may have grown locally beyond Gerota’s fascia or directly into the adrenal gland on the same side.
So this is why I mentioned Gerota’s fascia earlier.
If the cancer has extended beyond that membrane, it can be classified as stage 4, even without distant metastasis.
Now, the important thing to understand is that treatment is different for different stages.
So please ask your doctor which stage you have and what that means for your treatment.
Do Kidney Cancer Patients Need Genetic Testing?
Now let’s talk about genetic testing.
The question here is whether you were born with a genetic change that increases your chances of developing kidney cancer.
This is what we call germline genetic testing.
Not every patient with kidney cancer needs genetic testing.
But there are certain situations where we should consider it.
For example, if you are diagnosed with kidney cancer at a younger age, particularly at 46 years or younger, genetic evaluation should be considered.
The same applies if you have a strong family history.
Suppose your father or brother had kidney cancer, and now you have also developed kidney cancer.
In that situation, I would strongly consider genetic evaluation.
Another situation is when a patient has tumors in both kidneys.
Or maybe the patient has multiple kidney tumors at the same time.
Or somebody had kidney cancer a few years ago and now develops another kidney tumor.
These are situations where we should think about hereditary kidney cancer.
So the question you should ask your doctor is:
Do I need genetic testing?
Is Biopsy Necessary Before Kidney Cancer Surgery?
Now, in most other cancers, when we find a suspicious mass, we usually perform a biopsy.
But kidney cancer is a little different.
In many patients with a solid kidney mass that looks highly suspicious for cancer on CT or MRI, we may proceed directly to surgery without doing a biopsy.
Why?
Because the imaging appearance may be sufficiently characteristic, and the result of a biopsy may not change our decision to operate.
But there are situations where a biopsy is important.
For example, suppose a patient has a kidney mass and the scans suggest that cancer has already spread to other parts of the body.
In that situation, we may need a biopsy to confirm the diagnosis before starting medicines.
Another situation is when we are considering ablation or when the biopsy result may change the treatment plan.
So not every kidney tumor requires a biopsy, and not every kidney tumor should be operated on without one.
The decision depends on the clinical situation.
The question I would ask is:
“Do I need a biopsy, or can we proceed directly to surgery?”
What Are the Different Types of Kidney Cancer?
Now, let’s talk about the different types of renal cell carcinoma.
If you have already undergone surgery or a biopsy, you may have received a histopathology report.
That report tells us what type of kidney cancer you have.
You cannot reliably determine the exact histological type just by looking at a CT scan or MRI.
For that, we need tissue examination.
Clear Cell Renal Cell Carcinoma
By far, the most common type is clear cell renal cell carcinoma.
It accounts for approximately 70–75% of renal cell carcinomas.
And the reason this is important is that most of the major clinical trials and treatment studies have been performed in patients with clear cell renal cell carcinoma.
So much of the treatment data we have comes from this group.
Papillary Renal Cell Carcinoma
The next common type is papillary renal cell carcinoma.
It accounts for approximately 10–15% of cases.
Chromophobe Renal Cell Carcinoma
Another type is chromophobe renal cell carcinoma.
This accounts for around 5% of cases.
Papillary and chromophobe cancers are generally grouped under non-clear cell renal cell carcinoma.
And the reason I want you to know these terms is that the treatment, especially the medicines used in advanced disease, can differ depending on the type.
Rare Types of Kidney Cancer
There are also some rare types, including collecting duct carcinoma and renal medullary carcinoma.
These are uncommon, but I am mentioning them because their treatment can be quite different from the more common types.
So it is important to know exactly what type of cancer your pathology report shows.
What Do Sarcomatoid and Rhabdoid Features Mean?
Now, there are two more terms that I want you to become familiar with.
One is sarcomatoid, and the other is rhabdoid.
If your pathology report mentions sarcomatoid or rhabdoid features, it generally means that the tumor has more aggressive characteristics.
This is important because these tumors may behave differently and may require a different treatment approach.
So when you receive your histopathology report, ask your doctor:
What type of renal cell carcinoma do I have?
And also:
“Does my tumor have sarcomatoid or rhabdoid features?”
These are important questions.
Which Doctors Treat Kidney Cancer?
There are mainly two specialists involved in kidney cancer treatment.
The first is a urologist or uro-oncologist.
These are the surgeons who evaluate kidney tumors and perform operations such as partial nephrectomy or radical nephrectomy.
The second is a medical oncologist.
Medical oncologists treat cancer using medicines, including targeted therapy and immunotherapy.
So depending on the stage of the cancer, a patient may need treatment from one or both specialists.
How Do Doctors Decide Whether Kidney Cancer Is High Risk or Low Risk?
Now, I want to explain something called risk stratification.
This is particularly important in patients with advanced or metastatic kidney cancer.
We look at certain clinical findings and blood tests to understand whether the cancer is likely to behave more aggressively.
One important factor is the patient’s performance status.
What does that mean?
Suppose a patient is very weak, spends most of the day in bed or is unable to perform normal activities.
That patient has a poor performance status.
And generally, this is not a favorable sign.
Then we look at blood tests.
For example, if the blood calcium level is elevated, that is one risk factor.
If the patient has anemia, meaning low hemoglobin, that is another risk factor.
We also look at neutrophils, which are a type of white blood cell.
If the neutrophil count is elevated, that can be another risk factor.
And if the platelet count is elevated, that is another factor.
We also consider the time between diagnosis and the start of systemic treatment.
These factors are used in a commonly applied risk classification called the IMDC model for metastatic renal cell carcinoma.
An older classification also included LDH, but LDH is not part of the standard IMDC criteria.
Based on these factors, patients are classified into favorable, intermediate or poor-risk groups.
And this matters because the choice of medicines and the expected treatment outcomes can vary according to the risk group.
So the question I would ask my doctor is:
“Am I in the favorable, intermediate or poor-risk category?”
What Are the Treatment Options for Kidney Cancer?
Now, let’s discuss the treatment options available for renal cell carcinoma.
There are several options, and the treatment depends on the stage of the disease, the patient’s health and the type of kidney cancer.
Sometimes we may simply observe a small kidney tumor.
In other patients, we perform surgery.
Another option is ablation, where we destroy the tumor using heat or freezing.
And for advanced kidney cancer, we have medicines, including targeted therapy and immunotherapy.
Let’s discuss these one by one.
Can a Kidney Tumor Be Observed Without Surgery?
Yes, sometimes.
This may sound surprising because when somebody hears the word cancer, the first thought is that it must be removed immediately.
But not every small kidney mass needs immediate surgery.
For example, suppose an elderly patient has a very small kidney tumor.
The patient also has significant heart disease, lung disease or other medical problems.
Now, if we think that the risk of surgery may be greater than the risk from that small tumor, we may decide to monitor it.
This is called active surveillance.
We perform imaging at regular intervals to see whether the tumor is growing or changing.
So active surveillance does not mean that we are ignoring the tumor.
It means we are monitoring it carefully and deciding when treatment may be required.
Of course, this option is not suitable for every patient.
What Is Ablation Treatment for Kidney Cancer?
Another option for selected small kidney tumors is ablation.
Instead of removing the tumor surgically, we insert a special probe into the tumor, usually under CT or ultrasound guidance.
The tumor can then be destroyed using heat or freezing.
For example, radiofrequency or microwave ablation uses heat, while cryoablation uses freezing.
These treatments may be considered in selected patients, particularly when surgery carries a higher risk.
But again, not every kidney tumor is suitable for ablation.
The size, location and other characteristics of the tumor are important.
Kidney Cancer Surgery: Partial Nephrectomy or Radical Nephrectomy?
Now, let’s discuss surgery.
I want you to pay particular attention to this section if you have been diagnosed with a kidney mass and have not yet undergone surgery.
Today, many kidney cancer operations can be performed using minimally invasive techniques.
These include laparoscopic and robotic surgery.
The surgeon performs the operation through small incisions rather than one large incision.
And the advantage is that, in appropriately selected patients, postoperative pain and recovery time may be reduced.
In the past, many kidney operations required a large incision, and patients often took longer to recover.
Now, with laparoscopic and robotic techniques, many patients recover relatively quickly.
But the important thing is that the surgeon has two main options.
One is partial nephrectomy, where we remove only the tumor-bearing portion of the kidney.
The other is radical nephrectomy, where we remove the entire kidney.
And as a general rule, when it is safe and technically possible, we prefer to preserve the kidney.
What Is Partial Nephrectomy?
Partial nephrectomy means removing the tumor along with a small margin of surrounding tissue while preserving the remaining healthy kidney.
Why do we prefer this?
Because the kidney has an important function.
It filters our blood, removes waste products and maintains fluid and electrolyte balance.
So if we can remove the cancer and preserve the healthy kidney, that is often beneficial for the patient.
Let me give you an example.
Suppose you have a tumor in your right kidney.
If we remove the entire right kidney, you will be dependent on your left kidney.
Now, most people can live normally with one healthy kidney.
But suppose years later you develop a problem in the left kidney.
Maybe you develop kidney disease, or in a small number of patients, another kidney tumor.
Then preserving kidney tissue during the first surgery could become very important.
This is one of the reasons we prefer partial nephrectomy whenever it is oncologically safe and technically feasible.
Of course, sometimes the tumor is too large or located in such a position that partial nephrectomy may not be possible.
So the question I would ask my surgeon is:
“Am I a candidate for partial nephrectomy?“
Laparoscopic Partial Nephrectomy
In laparoscopic partial nephrectomy, the surgeon performs the operation through small incisions using a camera and specialized instruments.
The tumor is removed while preserving the remaining kidney.
This is a technically demanding operation because we need to remove the tumor, control bleeding and repair the kidney.
And at the same time, we want to preserve as much healthy kidney tissue as possible.
Robotic Partial Nephrectomy
Robotic partial nephrectomy is another minimally invasive approach.
Here, the surgeon uses a robotic surgical system to perform the operation.
The robotic system provides a magnified three-dimensional view and instruments with a wide range of movement.
This can be useful, particularly when we are operating on a tumor that is located deep inside the kidney or close to important blood vessels.
But I want to clarify one thing.
The robot does not perform the surgery on its own.
The surgeon controls the robotic instruments throughout the operation.
And not every patient requires robotic surgery.
Both laparoscopic partial nephrectomy and robotic partial nephrectomy are established options in selected patients.
What Is Radical Nephrectomy?
Sometimes the tumor is very large or involves a major portion of the kidney.
In such cases, removing only the tumor may not be safe or feasible.
So we may need to remove the entire kidney.
This operation is called radical nephrectomy.
It can be performed through open, laparoscopic or robotic surgery, depending on the tumor and the patient.
In laparoscopic radical nephrectomy, we remove the kidney using small incisions and laparoscopic instruments.
In robotic nephrectomy, we use a robotic surgical system.
The main aim is to remove the cancer safely.
And if the opposite kidney is healthy, most patients can live a normal life with one kidney.
However, kidney function and blood pressure should be monitored after surgery.
Laparoscopic and Robotic Kidney Cancer Surgery in Indore
For patients looking for kidney cancer surgery in Indore, one of the most important things is to understand whether the kidney can be preserved.
Many patients come with a CT scan showing a kidney mass, and their first question is, “Doctor, do you need to remove my entire kidney?”
The answer depends on the tumor.
We need to look at the size, location and relationship of the tumor to the blood vessels and collecting system of the kidney.
Sometimes a small tumor can be removed with laparoscopic partial nephrectomy or robotic partial nephrectomy.
In other patients, laparoscopic radical nephrectomy or robotic nephrectomy may be required.
And sometimes open surgery may be the safer option.
So when deciding between laparoscopic kidney cancer surgery and robotic kidney cancer surgery, the important thing is not simply the technology.
The important thing is complete cancer removal, preserving kidney function whenever possible and choosing the safest approach for the patient.
What About Medicines for Kidney Cancer?
Now, let’s get into medications.
There are many medication options available for renal cell carcinoma, particularly when the cancer is advanced or has spread to other organs.
You don’t need to memorize the names of all these medicines.
I just want you to know that there are several treatment options available.
One group is called tyrosine kinase inhibitors, or TKIs.
These are targeted therapy medicines, many of which are available as tablets.
Another important group is immunotherapy.
These medicines help the immune system attack cancer cells.
Some patients receive immunotherapy alone in specific settings, while others receive combinations of immunotherapy medicines or immunotherapy with targeted therapy.
And in certain patients who have undergone kidney cancer surgery, additional treatment may be considered to reduce the risk of recurrence.
The selection of medicines depends on the type of kidney cancer, the stage, the patient’s risk category and previous treatment.
So the important question is not simply which is the newest medicine.
The important question is which treatment is appropriate for your particular cancer.
Questions I Would Ask My Doctor if I Had Kidney Cancer
If I were diagnosed with kidney cancer, these are some of the questions I would want answered:
1. What stage of kidney cancer do I have?
2. Is the cancer limited to my kidney, or has it spread?
3. Do I need a biopsy before treatment?
4. What type of renal cell carcinoma do I have?
5. Does my pathology report show sarcomatoid or rhabdoid features?
6. Do I need genetic testing?
7. Am I a candidate for partial nephrectomy?
8. Can my surgery be performed laparoscopically or robotically?
9. If the entire kidney is removed, how will it affect my kidney function?
10. Do I need targeted therapy or immunotherapy?
11. What is my risk of recurrence?
12. What follow-up scans and blood tests will I need?
These are the questions I think patients should discuss with their treating doctors.
Final Words
Kidney cancer is not the same in every patient.
Some patients have a small tumor limited to the kidney, while others may have more advanced disease.
And treatment is going to vary depending on the stage, type of cancer and general condition of the patient.
In some patients, we can preserve the kidney by performing partial nephrectomy.
In others, removing the entire kidney may be necessary.
And for advanced kidney cancer, newer medicines have improved the treatment options considerably.
So if you or somebody in your family has been diagnosed with a kidney tumor, the first thing is to understand the stage and the available treatment options.
And don’t hesitate to ask your doctor questions.
Because the more you understand your disease, the better prepared you will be to make decisions about your treatment.
Dr. Yusuf Saifee
Consultant Urologist & Uro-Oncologist
Laparoscopic & Robotic Surgeon
Kidney Transplant Surgeon
Indore & Mumbai
For kidney cancer evaluation, laparoscopic or robotic kidney cancer surgery, or a second opinion regarding kidney-preserving surgery:
Website: www.dryusufsaifee.com
This article is intended for general patient education. Treatment decisions should be made after individual clinical evaluation.